


“No practitioner of medicine should be without a sphygmomanometer.”
J. W. Fisher, medical director of the Northwestern Mutual Life Insurance Company, said that to the Association of Life Insurance Medical Directors on 4 October 1911. His paper was about blood pressure readings in examinations for life insurance, and it reported that the people his company had insured at ages 55 to 60 averaged about 134 systolic.

He wasn’t alone. A few American life insurers had begun measuring systolic pressure in 1906. A history in the journal Hypertension credits the industry with early and consistent evidence that higher pressures mattered clinically. That was four decades before the Framingham Heart Study began.
These old papers are worth reading now because the line has just moved again. In August 2025 the American Heart Association and the American College of Cardiology recommended medication for adults whose blood pressure averages 130/80 or higher even when their risk of heart disease and stroke is low, after three to six months of trying to bring it down by changing habits. The 2017 guideline had told lower-risk adults to wait until 140/90.
One analysis in Hypertension put the number of extra American adults who could now be told to take pills at 26.8 million, half of them aged 18 to 39. Its authors say single-visit readings may inflate that figure.
Where was the line before any of this?
In 1932, Franklin D. Roosevelt’s campaign office released his medical records. His blood pressure was 140/100, and according to a 2014 history in The Lancet, co-written by Framingham investigators, it “did not prompt any medical intervention”. By 1941 it was 188/105. His personal physician, Ross McIntire, was an ear, nose and throat specialist. He insisted that the President was healthy and that his blood pressure was “no more than normal for a man of his age”.
Roosevelt died on 12 April 1945, aged 63, of a cerebral hemorrhage. His blood pressure at the end was 300/190.
Today the 1932 reading alone would count as stage 2 hypertension.
The textbooks backed that kind of restraint. In the 1931 edition of Heart Disease, the eminent Boston cardiologist Paul Dudley White called treating hypertension “a difficult and almost hopeless task in the present state of our knowledge”, and suggested the raised pressure might be a compensatory mechanism best not tampered with, as Elias and Goodell quote him in the Journal of Clinical Hypertension.
Then there’s the rule of thumb in the headline. George Comstock of the US Public Health Service set it down in 1957. All the early researchers, he wrote, had seen average systolic pressure rise with age, and the rough guide to expected systolic pressure became “100 plus the subject’s age in years”.
So a 60-year-old was expected to sit at 160.
The Framingham Heart Study began in 1948, three years after Roosevelt’s death, and White, with David Rutstein of Harvard, pushed for it to be based in that town. It enrolled 5,209 men and women aged 30 to 62 who had no signs of heart disease yet, and brought them back every two years to be examined.
In 1957 the study reported its first major results. People with blood pressure of 160/95 or more had nearly four times the incidence of coronary heart disease.
Boston University, the study’s partner since 1971, wrote in February 2025 that Framingham was behind “identifying the fundamental risk factors for heart disease”.
David S. Jones, who chairs Harvard’s Department of the History of Science, puts it more carefully. “I think it would be hard to say that any one researcher or study identified those risk factors,” he wrote. Various people had suspected them for a while, and on blood pressure he points back to the insurers, who he thinks likely deserve the credit for seeing it as a problem. Framingham, in his view, popularized the phrase “risk factor” and made those classic risk factors better known to the public.
That matches what I found in the old papers. The insurers had the numbers first. What Framingham added was evidence doctors would eventually accept, and that took a long time.
The 1957 result didn’t change much in practice at first. Many doctors went on treating 100 plus the patient’s age as a permissible systolic pressure, the Lancet history says, because the profession was unsure that population studies could be trusted. When the drug propranolol was first studied in 1964, the “normotensive” control groups included patients with systolic pressure as high as 170.
By 1971, with 14 years of follow-up, Framingham’s investigators were writing of “mounting evidence that many of the commonly accepted beliefs concerning hypertension and its cardiovascular consequences may be in error”. The study had shown that high blood pressure was not benign or compensatory, two of its investigators later wrote, and that pressure rising with age was not normal. In 1977 the first report of the Joint National Committee made blood pressure control part of practice guidelines.
Since then the threshold has only come down. In 2003, JNC 7 created “prehypertension” for readings of 120 to 139 systolic or 80 to 89 diastolic, citing risk at levels previously considered normal. In 2017, the two cardiology groups lowered the threshold for hypertension from 140/90 to 130/80, which by their estimate raised the share of US adults with hypertension from 32% to 46%.
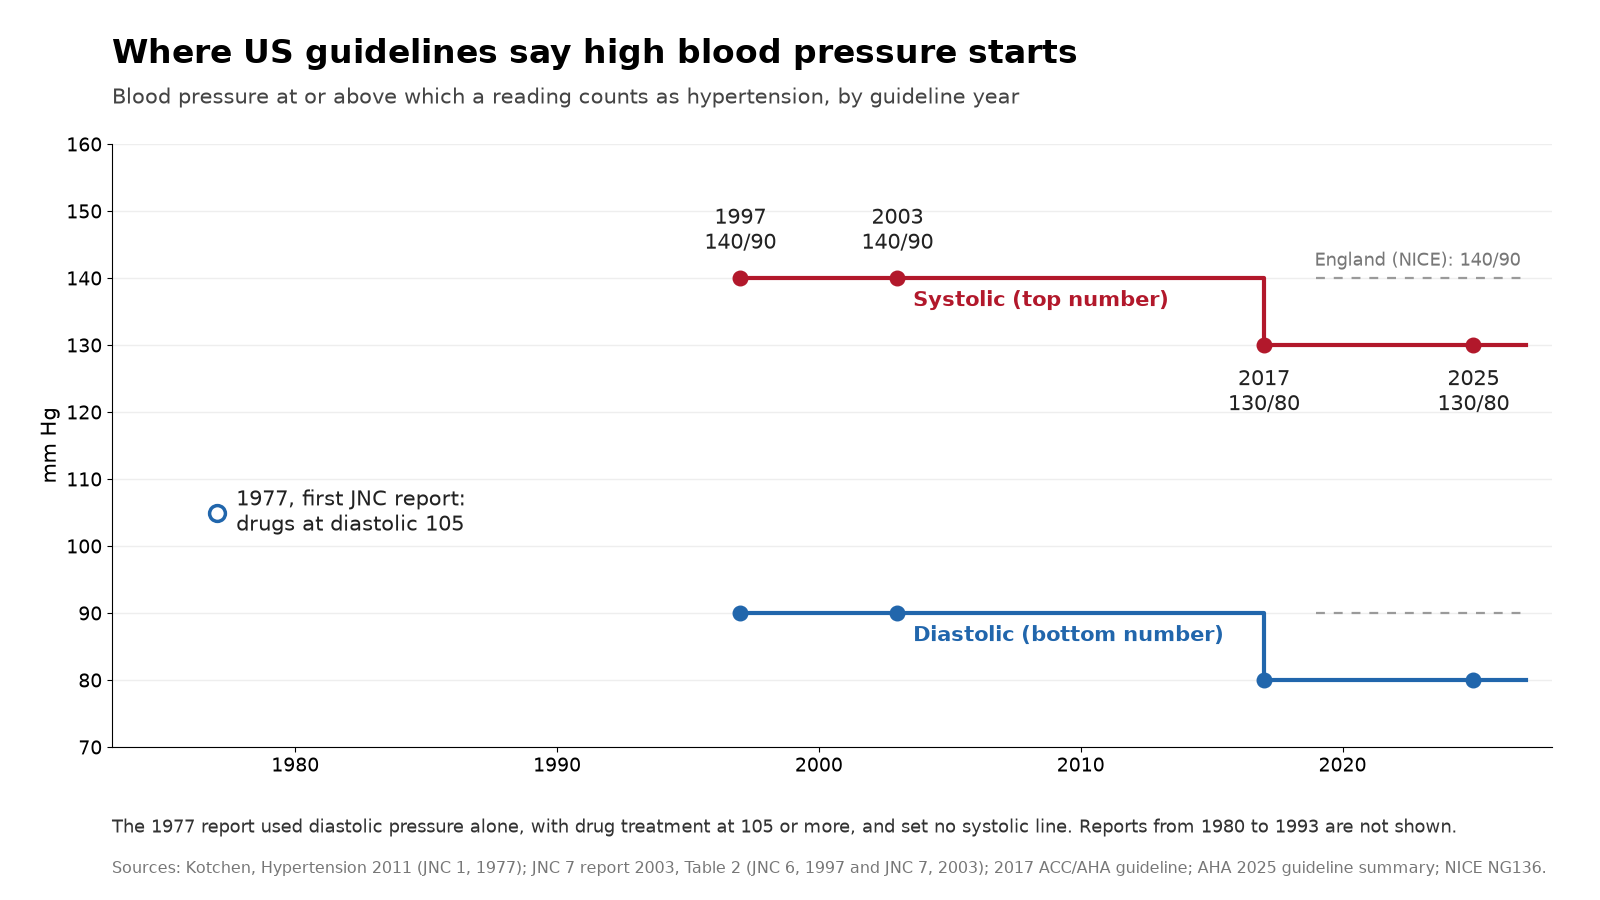
The family doctors have held back. The American Academy of Family Physicians declined to endorse the 2017 guideline, and in October 2025 it stopped short of endorsing the new one, saying its target of below 130/80 for everyone and its drug treatment at lower thresholds don’t fully match the academy’s own advice. Its 2022 guideline aims for below 140/90.
Take a clinic reading of 136/84. Under the American guideline’s categories, that’s stage 1 hypertension. In England, NICE doesn’t start a diagnosis until a clinic reading reaches 140/90.
