

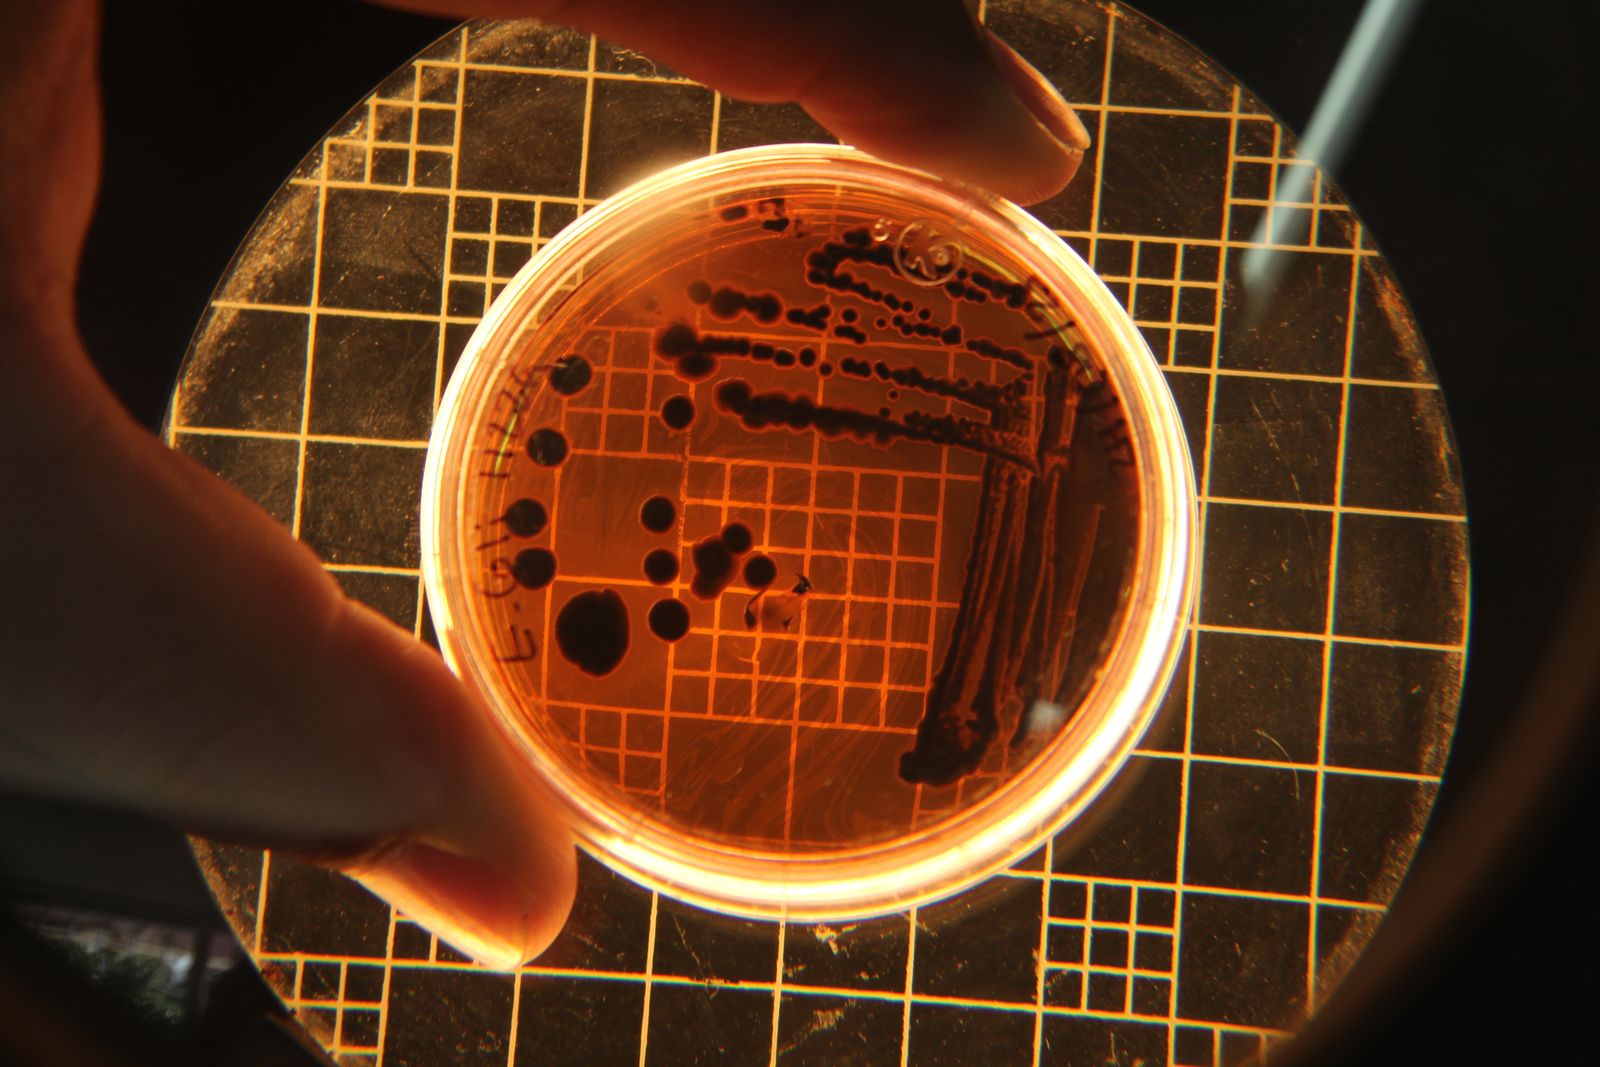
On September 3, 1928, Alexander Fleming returned from holiday to his laboratory at St. Mary’s Hospital in Paddington, London, and began sorting through plates of Staphylococcus. On one dish, a mold colony had appeared. Immediately around it was a clear zone where the bacteria had failed to grow. The American Chemical Society’s historical account dates Fleming’s return and observation to September 3, rather than the September 28 date repeated in many later retellings.
The contaminated plate did not instantly produce a usable medicine. That would take another decade, an Oxford research team, wartime improvisation, and industrial fermentation on two continents. But the clear halo was the opening image of the modern antibiotic era. One frequently cited estimate, repeated by Popular Science and Oxford’s Dunn School, is that penicillin has saved more than 500 million lives.

A messy bench and an unexpected contaminant
Fleming was already an established bacteriologist, although not yet a global celebrity. He also had a reputation for keeping cultures long enough to inspect unexpected changes rather than immediately clearing every used dish from his bench.
Before leaving for his holiday, he had prepared plates containing Staphylococcus, bacteria associated with boils, abscesses, wound infections, and sepsis. During his absence, one plate became contaminated with a blue-green mold.
Later historical reconstructions have often connected the contaminating strain to work being done by mycologist C. J. La Touche in a laboratory below Fleming’s. The exact route taken by a single microscopic spore, however, cannot be reconstructed with certainty. The familiar story of a spore simply blowing through an open window should therefore be treated as a vivid possibility, not a documented fact.
The mold was historically identified as Penicillium notatum. Modern taxonomic work generally classifies Fleming’s strain as Penicillium rubens. Whatever its name, the important feature was the clear agar surrounding it: something produced by the fungus was inhibiting nearby bacteria.
What Fleming actually recognized
Contaminated cultures were an ordinary laboratory nuisance. Mold suppressing bacterial growth was not wholly unknown, either. Fleming’s contribution was to stop, investigate the anomaly, test the mold’s effects, and give its antibacterial substance a name.
He grew the fungus separately and studied the liquid surrounding it, initially referring to the substance as mould juice. He found that it inhibited several disease-causing bacteria, including staphylococci, streptococci, meningococci, and the diphtheria bacillus. He eventually called the substance penicillin.
Fleming photographed the plate and continued working with the mold. Recollections say that he reacted to the unusual dish with an understated observation that it was funny or curious. The exact wording matters less than what followed: he did not rinse the contamination away.
An eye trained to notice the odd
Fleming also made pictures with microbes, arranging naturally pigmented bacteria on agar to produce small figures and scenes. The results were temporary because the organisms continued growing until their boundaries blurred.
It is tempting to say that this microbial art trained him to see the contaminated plate differently. That cannot be proved, but it fits a broader pattern in his work: Fleming paid attention to irregular colonies, clear zones, and cultures that behaved in ways they were not supposed to.
An earlier accident had already rewarded that habit. In 1921, nasal mucus introduced into a bacterial culture produced another clear area. Fleming’s investigation led to lysozyme, an antibacterial enzyme found in tears, saliva, mucus, and other secretions.
Lysozyme was scientifically valuable but weak against many of the bacteria responsible for severe human infections. Penicillin was different. It acted against organisms associated with some of the most feared infections of the era.
Why the discovery almost stalled
Fleming published his findings in the British Journal of Experimental Pathology in 1929. The paper did not trigger an immediate medical revolution. Penicillin was unstable, difficult to concentrate, and hard to produce in useful quantities. Fleming and his colleagues could prepare crude solutions, but they could not turn the substance into a reliable systemic medicine.
By the late 1930s, the crucial work had shifted to Oxford. Australian pathologist Howard Florey led a team that included German-born biochemist Ernst Chain, Norman Heatley, Edward Abraham, Margaret Jennings, and other researchers at the Sir William Dunn School of Pathology.
Chain helped extract material with antibacterial activity. Heatley developed assays and extraction methods that allowed the team to recover and measure penicillin more effectively. In 1940, animal experiments showed that the substance could protect mice from otherwise lethal streptococcal infection.
The first patient to receive the Oxford team’s penicillin systemically was Albert Alexander, a police officer suffering from a severe infection. The often-repeated claim that his illness began with a rose-thorn scratch is not secure: the University of Oxford says there is no evidence for the rose-thorn story and points instead to evidence that Alexander may have been injured during a wartime bombing incident.
On February 12, 1941, Alexander received penicillin and improved dramatically. His temperature fell and the infection began to recede. But the team had too little of the drug. Researchers recovered penicillin from his urine and reused it, yet the supply was exhausted after several days. Alexander relapsed and died on March 15.

From laboratory curiosity to wartime medicine
The problem was no longer whether penicillin worked. It was whether anyone could make enough of it.
In the summer of 1941, Florey and Heatley travelled to the United States and made contact with the Department of Agriculture’s Northern Regional Research Laboratory in Peoria, Illinois. Researchers there found that corn-steep liquor, a by-product of cornstarch manufacturing, could sharply increase penicillin yields.
A search for more productive molds also produced one of the story’s most memorable details: a particularly useful strain was found on a moldy cantaloupe bought at a Peoria market. Researchers then produced still more productive variants through mutation and selection.
American pharmaceutical companies adapted deep-tank fermentation and rapidly expanded production. By D-Day in June 1944, Allied forces had substantial supplies available for infected wounds and other bacterial illnesses that had killed enormous numbers of soldiers in earlier wars.
Fleming, Florey, and Chain shared the 1945 Nobel Prize in Physiology or Medicine. The award captured three indispensable stages of the story: noticing and investigating the mold, reviving and purifying the compound, and proving that it could become a medicine. It inevitably simplified the contributions of Heatley and the larger British and American teams that made mass production possible.
What penicillin does to bacteria
Penicillin belongs to the beta-lactam family of antibiotics. It binds to proteins that bacteria use to cross-link peptidoglycan, the mesh-like material that gives a bacterial cell wall its strength.
When those cross-links fail, the wall weakens and susceptible bacterial cells can rupture under internal pressure. Human cells do not possess peptidoglycan walls, which gives penicillin its selective action against bacteria rather than human tissue.
The genus Penicillium continues to attract researchers, but promising headlines require care. In 2016, scientists described Penicillium excelsum, a species found throughout the Brazil nut tree ecosystem in the Amazon. The accompanying FAPESP report did not establish that the new species had bactericidal activity. Lead researcher Marta Hiromi Taniwaki said the team did not yet know whether it produced substances of pharmaceutical interest. The report separately noted that another species, P. glabrum, produces a compound with bactericidal activity.
The arms race Fleming warned about
During his 1945 Nobel lecture, Fleming warned that exposing microbes to doses too small to kill them could encourage resistance. His warning focused specifically on the danger of underdosing and exposing bacteria to non-lethal concentrations.
Resistance emerged rapidly as penicillin use expanded. Later generations of antibiotics repeatedly produced the same pattern: a drug kills susceptible bacteria, while organisms carrying protective mutations or resistance genes survive and spread.
The scale of the modern problem should not be confused with the toll from MRSA alone. The World Health Organization estimates that bacterial antimicrobial resistance overall was directly responsible for 1.27 million deaths worldwide in 2019 and contributed to millions more.
That is why the antibiotic story is not simply a sequence of new drugs defeating old diseases. It is an evolutionary contest involving prescribing, infection control, surveillance, diagnostics, vaccines, and the continuing search for new treatments.
What the halo meant
The enduring image is simple: a small fungal colony surrounded by a clear region where bacterial growth has disappeared. Fleming did not yet know the compound’s structure, how to purify it, or how factories might produce it by the kilogram. He only knew that something on the plate demanded an explanation.
Before effective antibiotics, an infected cut, pneumonia, complications of childbirth, or bacteria entering a surgical wound could become fatal with frightening speed. Penicillin did not eliminate that danger, but it changed the odds and helped make much of modern medicine possible.
Ninety-eight years after Fleming examined the contaminated dish, the antibiotic era is roughly the length of one long human life. The bacteria are still evolving. The drugs are still losing and regaining ground. And somewhere in a laboratory, someone is looking twice at a culture that is not behaving the way it should.